Tesamorelin

Overview

What is Tesamorelin?

Tesamorelin is an FDA-approved synthetic growth hormone-releasing hormone (GHRH) analog designed for treating HIV-associated lipodystrophy. This 44-amino acid peptide with a trans-3-hexenoic acid modification selectively reduces visceral adipose tissue while preserving subcutaneous fat, making it unique among growth hormone therapies.


Key Benefits

FDA-approved formulation, selective visceral fat targeting, proven clinical efficacy, standardized dosing

Mechanism of Action

Subcutaneous injection provides optimal bioavailability for GHRH receptor binding and pulsatile GH release stimulation

Pharmacokinetics

Peak: 9 min Half-life: 26 min Cleared: ~2.1 hrs

Research Indications

HIV-Associated Lipodystrophy

FDA-approved indication showing 15-20% visceral fat reduction in clinical trials

Selective Visceral Fat Targeting

Unique mechanism spares subcutaneous fat while reducing harmful visceral adiposity

Sustained Fat Loss

Maintained weight loss with continuous treatment over 52+ weeks in clinical studies

Triglyceride Reduction

12.3% triglyceride reduction demonstrated in pooled analysis of clinical trials

Cholesterol Profile Improvement

7.2% improvement in cholesterol/HDL ratio with daily 2mg dosing

NAFLD Treatment

37% liver fat reduction over 12 months in HIV patients with fatty liver disease

Lean Muscle Mass Preservation

Maintains muscle mass during fat loss, unlike conventional weight loss methods

Muscle Density Enhancement

Improved muscle composition and density through IGF-1 mediated mechanisms

IGF-1 Elevation

26% increase in IGF-1 levels supporting muscle growth and recovery processes

Research Protocols

Disclaimer

These are commonly discussed research protocols shared for educational reference. This is not medical advice and is not a substitute for guidance from a qualified healthcare provider.

GoalDoseFrequencyRoute
HIV Lipodystrophy (FDA Approved) 1.4 mg daily Once daily SubQ (abdomen)
Visceral Fat Reduction 2 mg daily Once daily SubQ (rotate sites)
Anti-aging/Body Composition 1-2 mg daily 5-7 days/week SubQ (evening)
NAFLD Treatment 2 mg daily Once daily SubQ for 12 months
Cognitive Enhancement (Research) 1 mg daily Once daily SubQ for 20 weeks
Research Protocol 1-2 mg daily Daily SubQ with cycle breaks

Timing

Evening injection aligns with natural growth hormone circadian rhythm. Take after dinner but before bedtime for optimal efficacy.

Peptide Interactions

Synergistic GH stimulation possible. Monitor IGF-1 levels closely and consider dose adjustments to prevent excessive growth hormone elevation.
Both bind to pituitary GHRH receptors. Combining saturates receptors without amplifying GH release, risking receptor desensitization and blunted pulsatility. Choose one based on your protocol goals.
Both target GHRH receptors but with conflicting release patterns. Tesamorelin promotes pulsatile GH release while DAC provides continuous stimulation, disrupting natural GH rhythms and accelerating receptor downregulation.
Similar GHRH mechanism but Tesamorelin has longer half-life. Low doses may be complementary, but higher doses risk excessive GH stimulation.
Tesamorelin increases diabetes risk (3.3-fold). Monitor blood glucose closely and adjust insulin doses as needed during treatment.
No direct interactions reported. May help mitigate glucose intolerance risk associated with Tesamorelin therapy.
Decreases corticosteroid effectiveness. Consider increasing steroid doses or using alternative anti-inflammatory therapy.
Somatostatin analog directly blocks GH release, completely negating Tesamorelin's therapeutic effects.
Redundant and potentially dangerous combination. Risk of acromegaly and metabolic complications from excessive GH exposure.

How to Reconstitute

Important

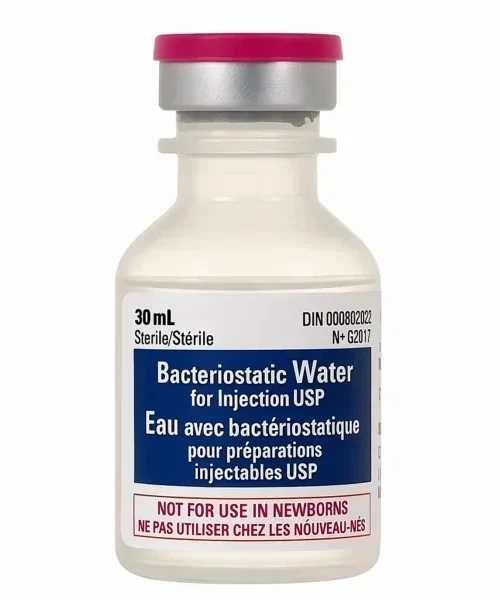
Always use bacteriostatic water (BAC). Sterile technique is essential.

  • 1
    Remove vial from refrigerator (powder should be stored at 2-8°C) and allow to reach room temperature
  • 2
    Egrifta SV: Add 0.5 mL sterile water to 2 mg vial
  • 3
    Egrifta WR: Add 1.3 mL bacteriostatic water to 11.6 mg vial
  • 4
    Gently swirl to dissolve - do not shake vigorously to prevent protein denaturation
  • 5
    Solution should be clear and colorless - do not use if cloudy or contains particles
  • 6
    Withdraw appropriate dose (typically 0.35 mL for 1.4 mg from SV preparation)
  • 7
    Inject subcutaneously in abdomen, rotating sites to prevent lipodystrophy
  • 8
    SV: Use immediately after mixing, discard any remaining solution. WR: Store at room temperature (20-25°C) for up to 7 days — do NOT refrigerate as it may cause precipitation

Quality Indicators

  • ✓

    FDA-approved formulations

    Egrifta SV or Egrifta WR from licensed pharmacy with proper documentation

  • ✓

    White crystalline powder

    Lyophilized powder should be white, uniform, and cake-like in appearance

  • ✓

    Clear reconstituted solution

    After mixing, solution should be clear and colorless without particles

  • ✓

    Proper packaging integrity

    Sealed vials with intact rubber stoppers and aluminum seals

  • X

    Discolored or cloudy solution

    Any yellow/brown color or cloudiness indicates degradation or contamination

  • X

    Visible particles or precipitate

    Particles indicate protein aggregation or bacterial contamination

  • !

    Compounded formulations

    Non-FDA approved compounded versions may have quality/potency variability

What to Expect

  • Week 1-2: IGF-1 levels begin to rise, possible mild water retention or joint discomfort

  • Week 4-6: Early metabolic changes, slight improvements in energy and sleep quality

  • Week 8-12: Visible visceral fat reduction begins, waist circumference may decrease

  • Week 12-26: Peak effects achieved with significant body composition improvements

Side Effects & Safety

  • Monitor blood glucose regularly - 3.3-fold increased diabetes risk documented
  • IGF-1 levels should be checked monthly - 47% exceed normal range at 26 weeks
  • Contraindicated in active malignancy or pituitary disorders
  • Common side effects include injection site reactions (17%) and joint pain (13%)
  • Development of diabetes or severe glucose intolerance (HbA1c ≥6.5%)
  • Signs of malignancy or suspicious growths
  • Severe hypersensitivity reactions or persistent injection site reactions
  • Excessive IGF-1 elevation (>2 SD above normal) with acromegaly symptoms

References

Cardiovascular Risk Assessment (2025)

Humans | 2 mg daily | 26 weeks | 0.40% reduction in 10-year ASCVD risk

Recent meta-analysis demonstrating cardiovascular risk reduction through improved metabolic parameters

View Study →

Anti-inflammatory Effects Study (2021)

Humans | 2 mg daily | 12 months | Reduced pro-inflammatory mediators

Comprehensive analysis showing reduced VEGFA, TGFB1, and CSF1 inflammatory markers beyond metabolic effects

View Study →

NAFLD Treatment Trial (2019)

Humans | 2 mg daily | 12 months | 37% liver fat reduction

Landmark study demonstrating significant hepatic fat reduction and prevented fibrosis progression in HIV patients with NAFLD

View Study →

Cognitive Enhancement Study (2012)

Humans | 1 mg daily | 20 weeks | Improved executive function and verbal memory

Randomized controlled trial showing favorable cognitive effects in both healthy older adults and those with mild cognitive impairment using 1mg daily dose

View Study →

CTR-1011 Extended Safety Study (2011)

Humans | 2 mg daily | 26-52 weeks | 69% achieved ≥8% VAT reduction

Long-term safety and efficacy study showing sustained visceral fat reduction with 69% responder rate vs 33% placebo

View Study →

LIPO-010 FDA Approval Trial (2010)

Humans | 2 mg subcutaneous daily | 26 weeks | 15.4% VAT reduction vs placebo

Pivotal Phase III trial demonstrating significant visceral adipose tissue reduction (-24 ± 41 cm² vs +2 ± 35 cm² placebo, p < 0.001) in HIV patients with lipodystrophy

View Study →